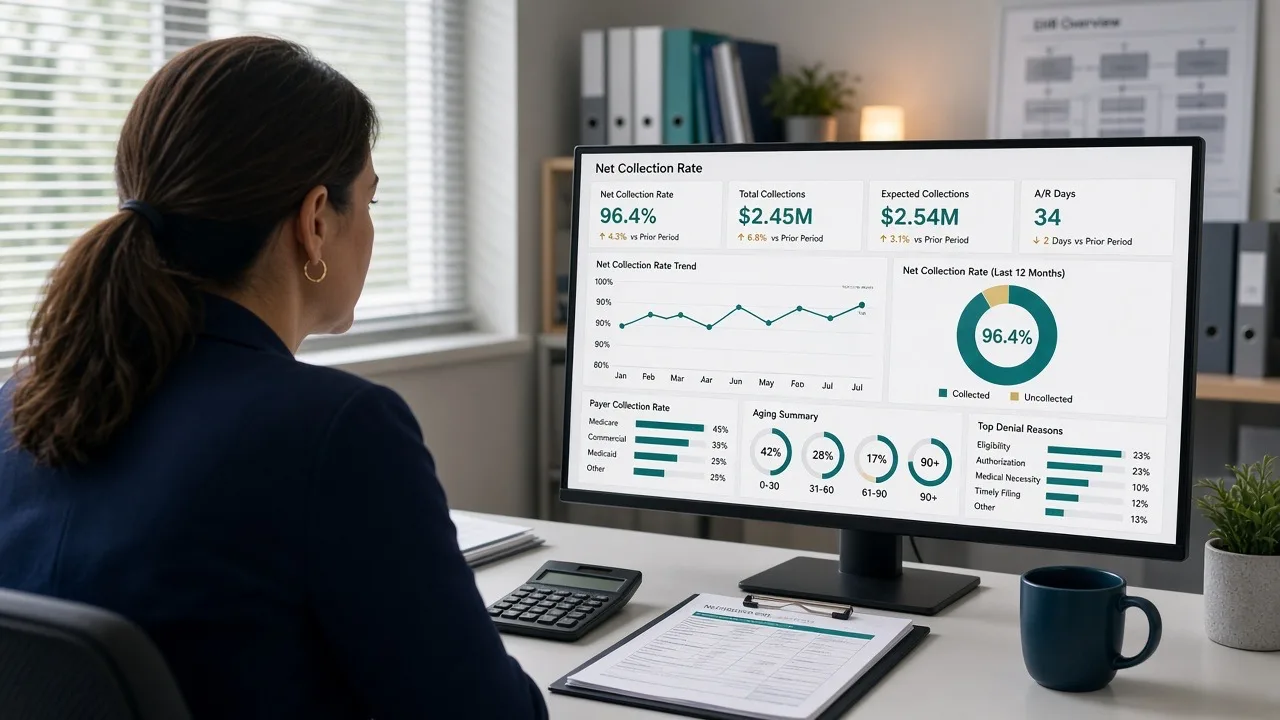
Collecting more revenue is only half the story. If it costs too much to get paid, your margin still shrinks.
Cost to collect measures how much a practice spends to bring in each dollar of collections. Practice owners and CFOs searching this KPI are usually comparing in-house billing vs outsourcing, pressure-testing staffing costs, or deciding whether denials and rework are quietly eating profit. That makes it one of the highest-converting revenue cycle topics in medical billing.
This guide explains the cost-to-collect formula, realistic 2026 benchmarks, common calculation mistakes, and the levers that lower cost without sacrificing net collection rate.
Quick Answer
Cost to collect = total billing and collection expenses ÷ total payments collected × 100.
A strong practice should:
- Include fully loaded labor, software, clearinghouse, statements, and vendor fees
- Target roughly under 3%–5% for many efficient physician practices (specialty and model dependent)
- Compare cost to collect with net collection rate, not fee percentage alone
- Reduce rework by raising clean claim rate and preventing denials
- Automate eligibility, scrubbing, posting, and routine follow-up where possible
- Review the metric monthly with denial rate and days in A/R
- Judge outsourcing partners on net yield after fees, not sticker price
A lower billing fee with weak collections can cost more than a stronger partner with a higher percentage.
Table of Contents
- What Cost to Collect Means
- How to Calculate It
- 2026 Benchmarks
- Common Mistakes
- How to Lower Cost to Collect
- Improvement Checklist
- When Support May Help
- FAQs
What Is Cost to Collect in Medical Billing?
Cost to collect answers one question: how much does it cost your organization to collect one dollar of payment?
It is an efficiency KPI, not a collections KPI. A practice can post a strong gross collection month and still have a poor cost-to-collect ratio if denials, manual rework, overtime, and statement cycles keep rising.
This metric sits beside other revenue cycle KPIs such as clean claim rate, denial rate, days in A/R, and net collection rate. Those metrics show whether money is coming in cleanly. Cost to collect shows what you spent to make it happen.
How to Calculate Cost to Collect Correctly
Formula:
Cost to collect = Total RCM operating costs ÷ Total payments collected × 100
Use the same measurement window for numerator and denominator — usually monthly with a rolling 90-day view.
What to Include in Costs
- Billing staff salaries, benefits, overtime, and contractor spend
- Practice management, clearinghouse, eligibility, and claim-edit software
- Outsourced billing or A/R vendor fees
- Patient statement printing, postage, portals, and payment processing fees tied to collections
- Training, QA, and management time allocated to billing operations
What Belongs in Collections
- Insurance payments posted
- Patient payments posted
Do not inflate the denominator with contractual adjustments. Cost to collect is about cash collected, not allowed amounts.
Accurate payment posting and complete expense tracking are required. If labor is undercounted, the KPI looks artificially strong.
What Is a Good Cost to Collect in 2026?
Benchmarks vary by specialty, scale, payer mix, and whether billing is in-house or outsourced. Useful working ranges for many practices:
- Under 3%: strong / highly efficient operations
- 3%–5%: common healthy range for well-run physician practices and many outsourced models
- 5%–8%: watch closely; often signals denial rework or incomplete automation
- Above 8%: urgent review of process, staffing, and technology
In-house teams often underestimate true cost because benefits, turnover, software, and management overhead are left out. Outsourced percentage fees look higher on paper until fully loaded in-house costs are compared honestly. Related reading: in-house vs outsourced medical billing.
Common Mistakes That Distort Cost to Collect
1. Counting Only Salaries
Software, clearinghouse fees, statements, and supervisor time belong in the numerator. Partial costing creates false confidence.
2. Ignoring Rework
Denied claims, corrected resubmissions, and aged A/R follow-up are expensive. If denial volume rises, cost to collect rises even when headcount stays flat.
3. Comparing Fee Percentage Alone
A 4% billing partner that lifts net collections can outperform a 3% partner that leaves denials and underpayments unworked. Always compare net yield after fees.
4. Separating Cost From Quality KPIs
Cheap billing that damages clean claim rate, days in A/R, or net collections is not inexpensive. Read cost to collect with those metrics together.
5. One-Month Snapshots
Seasonality, catch-up projects, and hiring spikes create noise. Use trend lines.
How to Lower Cost to Collect Without Hurting Cash Flow
The goal is lower cost per collected dollar — not fewer collections.
1. Prevent Denials at the Front End
Eligibility verification, authorization tracking, and claim scrubbing reduce expensive back-end rework. See eligibility verification, prior authorization, and claim scrubbing.
2. Raise First-Pass Acceptance
Every rejected or denied claim consumes labor twice. Improving clean claim rate is one of the fastest cost-to-collect levers.
3. Work Denials Fast and by Root Cause
Aging denials multiply touch points. Route by reason code, prioritize by dollars and deadlines, and feed patterns into prevention. See denial management and CARC codes.
4. Automate High-Volume Tasks
Eligibility checks, scrubbing, ERA import, and routine statusing should not consume senior biller time. Reserve skilled staff for complex appeals and underpayment recovery.
5. Strengthen Patient Collections Early
Point-of-service estimates and timely statements recover balances with fewer chase cycles. See patient collections.
6. Stop Avoidable Write-Offs
Writing off recoverable dollars can temporarily hide operating pain, but it destroys margin. Related: reducing write-offs and underpayment recovery.
Radiant RCM's Medical Billing Services and Revenue Cycle Consulting help practices lower cost to collect by cutting rework, tightening denial prevention, and reporting true collection yield.
Cost to Collect Improvement Checklist
- Define the formula and include fully loaded RCM costs
- Report monthly with a rolling 90-day trend
- Pair with net collection rate, denial rate, clean claim rate, and days in A/R
- Identify top denial reasons driving rework hours
- Measure average touches per claim and per denial
- Automate eligibility, scrubbing, and ERA posting where possible
- Set SLA for denial work within a few business days
- Review patient statement cadence and point-of-service collections
- Compare in-house fully loaded cost vs outsourced net yield
- Assign an owner to report cost to collect in leadership reviews
When Outside Support May Help
Your practice may need help when:
- Cost to collect stays above 5%–8% after internal cleanup
- Nobody can produce a fully loaded billing cost number
- Denial rework and aged A/R consume most staff time
- In-house vs outsourcing decisions are based on fee percentage alone
- Net collections look acceptable but margin is shrinking
- Leadership wants transparent KPI reporting tied to cost and yield
Radiant RCM supports healthcare practices with medical billing, denial prevention, A/R follow-up, patient collections support, and revenue cycle consulting built around measurable efficiency and yield.
Sensitive patient and insurance information should only be shared through approved and secure channels. Learn more about Radiant RCM's HIPAA compliance and information-handling approach.
Final Thoughts
Cost to collect shows whether your revenue cycle is efficient — not just active. Calculate it with fully loaded costs. Benchmark honestly. Cut rework through cleaner claims, faster denials, smarter automation, and earlier patient collections.
Practices that manage cost to collect beside net collection rate make better staffing and outsourcing decisions.
If your cost to collect is climbing while denials and rework keep rising, Radiant RCM can help. Request a demo to see how our billing workflows improve both efficiency and collected yield.
Frequently Asked Questions
What is cost to collect in medical billing?
Cost to collect is the percentage of collected payments spent on billing and collection operations. It measures how expensive it is to turn earned services into cash.
What is a good cost to collect for a medical practice?
Many efficient physician practices target roughly under 3%–5%, depending on specialty, scale, and billing model. Figures above 8% usually need urgent operational review.
How do you calculate cost to collect?
Divide total RCM operating costs by total payments collected, then multiply by 100. Include labor, software, clearinghouse, statement, and vendor costs for the same period.
Is a lower billing fee always better?
No. A lower fee with weaker net collections, slower A/R, or higher denial leakage can leave less money in the practice than a higher fee with stronger yield.
What usually raises cost to collect the most?
Preventable denials, manual rework, weak front-end verification, slow A/R follow-up, and incomplete automation are common drivers.
Can outsourcing lower cost to collect?
Yes, when the partner reduces rework, improves clean claims and denial recovery, and delivers higher net yield after fees. Compare fully loaded in-house cost to outsourced net results.
Privacy Notice: Please do not submit patient records, insurance information, medical details, claim files, or other protected health information through the public website form. Review the Radiant RCM Privacy Policy before submitting an inquiry.
This article provides general operational information. Cost-to-collect definitions and benchmarks vary by specialty, accounting method, and billing model. Confirm your internal cost allocation methodology before changing financial reporting or vendor decisions.